
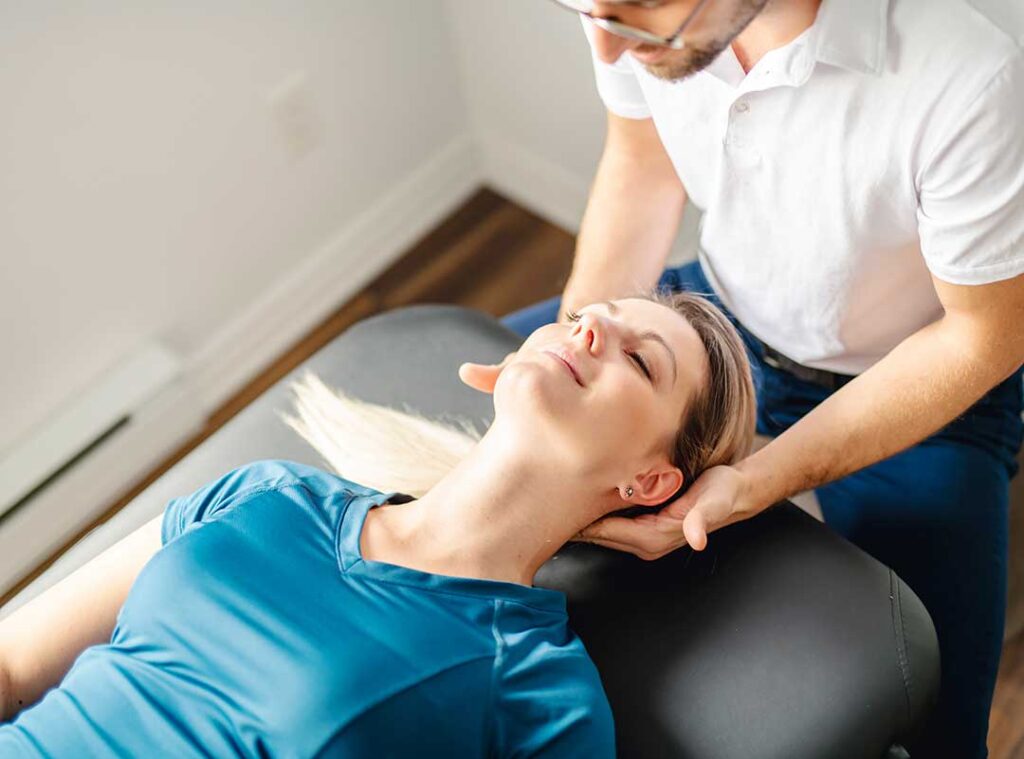
Spinal adjustments are controlled movements applied to joints of the spine to reduce pain, improve movement, and support normal physical function. The science behind them involves joint mechanics, the nervous system, muscle responses, and the way the brain processes pain.
An adjustment is not designed to “put a bone back in place” after every ordinary ache. In most cases, it is used as one part of care for musculoskeletal problems such as nonspecific low-back pain, stiffness, or certain types of neck discomfort.
What happens during a spinal adjustment?
A spinal adjustment uses a brief, carefully directed force on a spinal joint. The movement may be performed by hand or with a specialized instrument. The force can be quick and shallow, or slower and gentler, depending on the technique and the person’s condition.
The treatment is different from spinal mobilization. Mobilization uses gradual, controlled movement within a joint’s normal range. Manipulation, often called an adjustment, generally involves a short thrust that moves a joint slightly farther or faster than a person could comfortably move it alone.
A person may hear a popping sound. This sound usually comes from a rapid change in pressure within joint fluid, which can create gas bubbles. The sound does not mean that a bone has been “realigned,” and an audible pop is not required for treatment to have an effect.
How might an adjustment reduce pain?
The effects are probably explained by several overlapping processes rather than a single mechanical correction.
A joint that has become stiff or painful may respond to movement by improving its short-term range of motion. Stretching the joint capsule and surrounding tissues can also influence muscle tension. These changes may make ordinary movements—such as standing, walking, turning, or getting out of a chair—feel easier.
Spinal joints, muscles, ligaments, and skin contain sensory receptors that provide information to the nervous system. A controlled adjustment may change the signals coming from those tissues. In turn, the brain may temporarily reduce the intensity of pain signals or alter protective muscle guarding.
This does not mean pain is imaginary. Pain is a real protective experience produced through communication between the body and nervous system. The intensity of pain can be affected by inflammation, tissue sensitivity, sleep, stress, previous injuries, and expectations, as well as by joint movement.
Does an adjustment actually realign the spine?
Usually, no major structural realignment occurs from a single adjustment. The spine is a strong, flexible structure supported by muscles, ligaments, discs, and joints. Everyday posture also changes constantly with sitting, walking, lifting, and sleeping.
An adjustment may produce a temporary change in joint motion, muscle activity, or perceived stiffness. It should not be presented as permanently correcting a spine that is “out of place” in the ordinary sense.
Long-term improvement, when it occurs, is more likely to involve a combination of factors: gradual return to movement, strengthening, improved activity tolerance, education about pain, and changes in the factors that contributed to symptoms.
What conditions may respond?
Research provides the clearest support for spinal manipulation as one possible treatment for some forms of low-back pain, particularly pain that is not caused by a serious underlying disease or significant nerve compression. Benefits are generally modest and may be similar to those produced by other conservative treatments, including exercise-based care.
Some people with neck pain or certain headaches may also experience improvement, although the evidence varies by condition and technique.
An adjustment is less likely to address the underlying cause when symptoms result from a fracture, infection, inflammatory disease, cancer, severe nerve compression, or another condition requiring different medical care. It also does not repair a torn ligament, eliminate arthritis, or guarantee that pain will not return.
Why does treatment usually include more than an adjustment?
Pain often develops through a combination of restricted movement, deconditioning, repetitive tasks, sudden increases in activity, poor sleep, or prolonged positions. A passive treatment may help reduce symptoms, but lasting functional improvement usually depends on restoring comfortable movement and building capacity.
A broader plan may include:
- Gentle range-of-motion exercises
- Strengthening of the trunk, hips, or upper back
- Gradual return to work, walking, or recreational activity
- Advice on lifting, sitting, and pacing
- Sleep and stress considerations
- Medical evaluation when symptoms do not fit a routine musculoskeletal pattern
For residents managing long commutes, desk work, home maintenance, or seasonal outdoor tasks, symptoms may flare when activity rises sharply after a period of relative inactivity. A gradual approach is often more practical than trying to “catch up” in one weekend.
Are spinal adjustments safe?
For many adults, spinal manipulation performed by a trained and licensed practitioner causes only temporary effects, such as soreness, stiffness, tiredness, or a mild headache. These effects commonly resolve within a day or two.
Serious complications are rare, but they can occur. Neck manipulation deserves particular caution because rare reports have involved injury to blood vessels in the neck and stroke. Research has not fully settled whether manipulation causes these events or whether an underlying artery problem may already be producing neck pain or headache. Either way, sudden unusual symptoms require urgent medical attention.
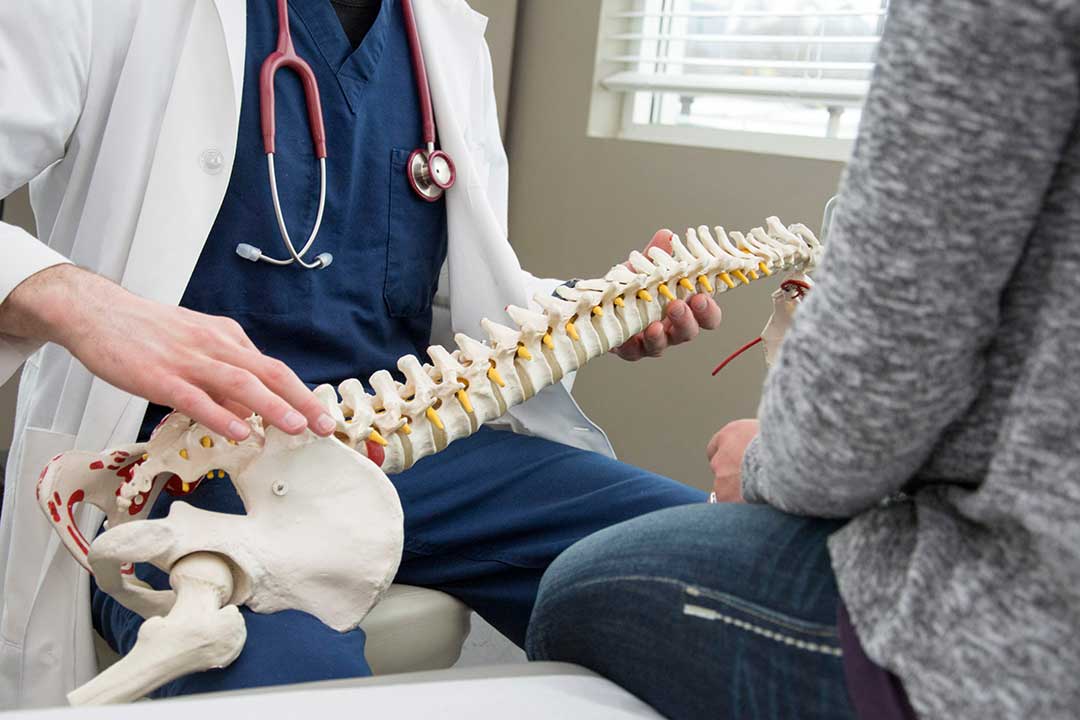
A careful health history matters. Extra caution or avoidance may be appropriate for people with severe osteoporosis, recent trauma, spinal cancer, certain inflammatory disorders, significant neurological symptoms, or previous spinal surgery. Pregnancy, blood-thinning medication, and other medical conditions should also be discussed before treatment.
What symptoms should not be treated as routine back or neck pain?
Prompt medical evaluation is more appropriate when pain occurs with warning signs such as:
- New or worsening weakness in an arm or leg
- Loss of bladder or bowel control
- Numbness around the inner thighs or genital area
- Fever, unexplained weight loss, or a history of cancer
- Severe pain after a fall, collision, or other injury
- A sudden, unusual headache or neck pain
- Difficulty speaking, facial drooping, fainting, or loss of balance
These signs may indicate a neurological, vascular, infectious, or structural problem that requires a different type of assessment.
What should a person expect from evidence-based care?
A sound evaluation should connect the symptoms with the examination findings and the person’s goals. Imaging is not automatically needed for ordinary back pain, especially when there are no warning signs. It may be considered when the history or examination suggests fracture, significant nerve involvement, infection, cancer, or another specific condition.
People should also be able to ask what the adjustment is intended to do, what alternatives exist, how many treatments may be reasonable to try, and what symptoms would require medical follow-up.
The most accurate view of spinal adjustments is neither that they are a cure-all nor that they have no value. They may provide short-term pain relief and improved movement for selected musculoskeletal problems, especially when combined with active rehabilitation and appropriate screening for conditions that need other care.
