

What does “subluxation” mean?
In Lynbrook, NY, residents may hear the word *subluxation* used in two different ways: as a medical description of a partially displaced joint, or as a chiropractic term describing altered spinal movement, alignment, or function.
These meanings are not interchangeable. In medicine, a subluxation generally refers to a partial loss of normal joint contact. It may result from trauma, arthritis, instability, or another structural problem. A true spinal subluxation in this sense can be serious, particularly when it involves the neck, spinal cord, or nearby nerves.
In chiropractic settings, “vertebral subluxation” has historically been used more broadly. It may refer to a combination of restricted movement, muscle tension, changes in joint mechanics, posture, or tenderness. The term does not always mean that a vertebra is visibly “out of place,” and it should not automatically be interpreted as a dangerous dislocation.
Why does the distinction matter?
The word matters because it can create confusion about what has actually been found.
A person may be told that a spinal segment is “subluxated” when the practical finding is reduced motion, muscle guarding, or irritation in a joint. That is different from a traumatic partial dislocation seen on imaging. The appropriate evaluation and treatment can differ substantially between these situations.
There is also no single universally accepted test for the broader chiropractic use of vertebral subluxation. A careful explanation should identify the specific findings involved, such as:
- Limited or painful movement
- Muscle tightness or guarding
- Local joint tenderness
- Changes in posture or movement patterns
- Numbness, tingling, or weakness
- Evidence of injury on imaging, when imaging is medically indicated
A useful discussion focuses less on the label and more on the measurable problem, its likely cause, and whether the proposed care is appropriate.
Does a subluxation mean a bone is out of place?
Usually, no—not in the dramatic sense many people imagine.
The spine naturally moves, bends, and adapts throughout the day. Small differences in joint position can occur with normal movement, muscle tension, fatigue, and posture. A sore or stiff back after lifting, driving, gardening, or sleeping awkwardly does not necessarily indicate that a vertebra has shifted out of position.
X-rays also require careful interpretation. Many posture and alignment differences are normal variations, and an image alone may not explain pain. Imaging is generally most useful when there is a history of significant trauma, neurological symptoms, suspected fracture, infection, cancer, or symptoms that persist or worsen despite appropriate care.
The phrase “put back into place” can therefore be misleading. Most ordinary mechanical back or neck pain is not caused by a bone that has completely left its normal position.
What symptoms might be associated with restricted spinal movement?
A person with a mechanically restricted spinal joint may notice localized pain, stiffness, muscle tightness, or discomfort with certain activities. Symptoms can develop after repetitive lifting, prolonged sitting, a minor strain, household work, exercise, or an awkward sleeping position.
For local residents, seasonal routines can contribute. Snow-related exertion, carrying wet clothing, moving storage items, yard work, and spending more time seated indoors during cold weather may increase strain on the back and neck. These factors may aggravate muscles and joints without proving that a subluxation is present.
Symptoms that radiate into an arm or leg may involve nerve irritation. Numbness, pins-and-needles sensations, reduced grip, foot weakness, or changes in balance deserve more attention than ordinary muscle soreness.
Pain severity alone does not identify the cause. A mild injury can be painful, while some significant conditions may begin with limited discomfort.
When could the problem be urgent?
Certain symptoms should not be attributed to a routine spinal restriction without medical evaluation. Prompt assessment is especially important after a fall, collision, direct blow, or other substantial injury.
Urgent warning signs include:
- New or worsening weakness in an arm or leg
- Loss of bladder or bowel control
- Numbness around the inner thighs or groin
- Severe neck pain after trauma
- Difficulty walking or maintaining balance
- Fever with significant back pain
- Unexplained weight loss or a history of cancer
- Severe pain accompanied by fainting, chest symptoms, or shortness of breath
- Sudden neurological symptoms such as facial weakness, trouble speaking, or severe dizziness
Neck manipulation requires particular caution in people with certain vascular, bone, neurological, or connective-tissue conditions. Serious complications are uncommon, but they can occur. A complete health history should be reviewed before any high-velocity spinal technique is considered.
How is a suspected subluxation evaluated?
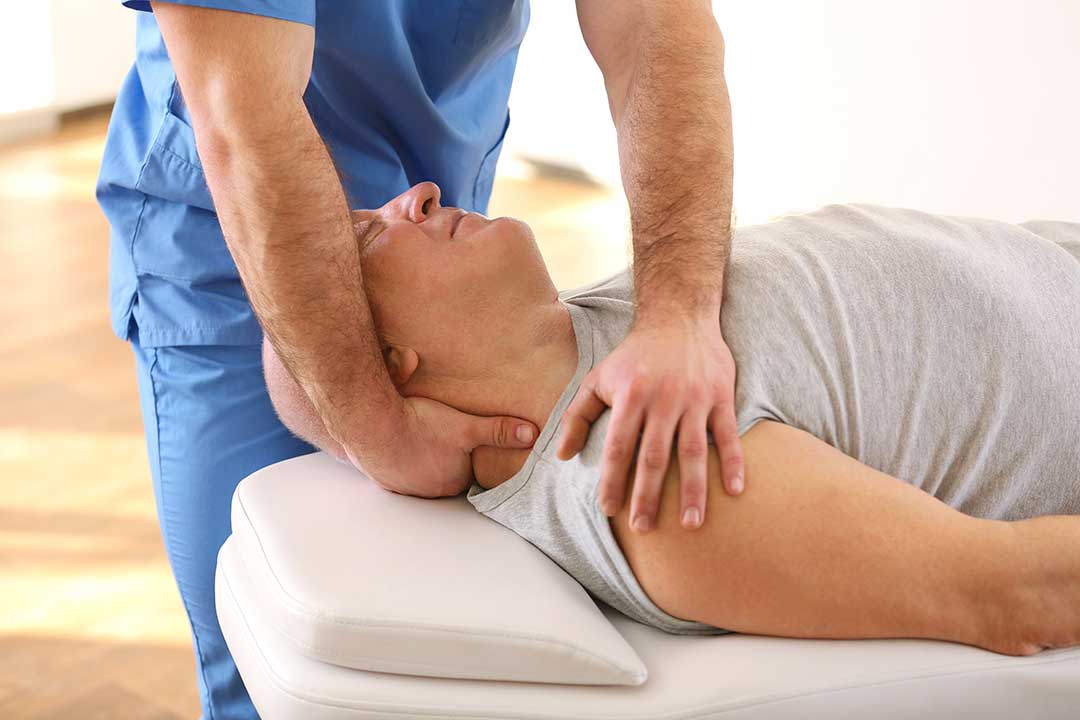
Evaluation usually begins with a history and physical examination. The clinician may ask when the symptoms began, whether there was an injury, what movements make them better or worse, and whether symptoms travel into an arm or leg.
The examination may include:
- Observation of posture and walking
- Testing active range of motion
- Strength, sensation, and reflex checks
- Assessment of muscle tenderness and joint movement
- Screening for signs that suggest nerve or spinal cord involvement
Imaging is not automatically necessary for ordinary back pain. It may be considered when there are red flags, significant trauma, persistent neurological symptoms, or a concern that cannot be assessed adequately through examination alone.
A responsible explanation should also include uncertainty. If the findings are nonspecific, the diagnosis should not be presented as more definite than the evidence allows.
Can spinal manipulation help?
Spinal manipulation may provide short-term relief for some people with uncomplicated mechanical low back pain or certain types of neck pain. Its potential benefit is generally discussed as one option among several, not as proof that a particular bone was severely displaced.
Treatment should be matched to the person’s symptoms, health history, and goals. Gentle movement, progressive exercise, activity modification, heat or cold, and other conservative approaches may also be considered depending on the situation.
Claims that a spinal subluxation causes broad internal disease, weakens the immune system, or explains unrelated health problems are not supported by reliable evidence. A spinal adjustment should not replace evaluation for symptoms that may come from infection, fracture, nerve compression, vascular disease, or another medical condition.
What questions should a resident ask?
Anyone hearing the term *subluxation* can ask for a plain-language explanation:
- What specific finding does the term describe?
- Is this a partial dislocation, limited motion, muscle tension, or something else?
- Was there an injury that could make the spine unstable?
- Are there signs of nerve or spinal cord involvement?
- Why is a particular treatment being recommended?
- What alternatives are available?
- What symptoms would require urgent medical attention?
- How will progress be measured?
The most useful diagnosis is one that connects symptoms with objective findings and leads to a safe, understandable plan. For residents and households in Lynbrook, that approach helps separate ordinary mechanical stiffness from conditions that need prompt medical attention.
